
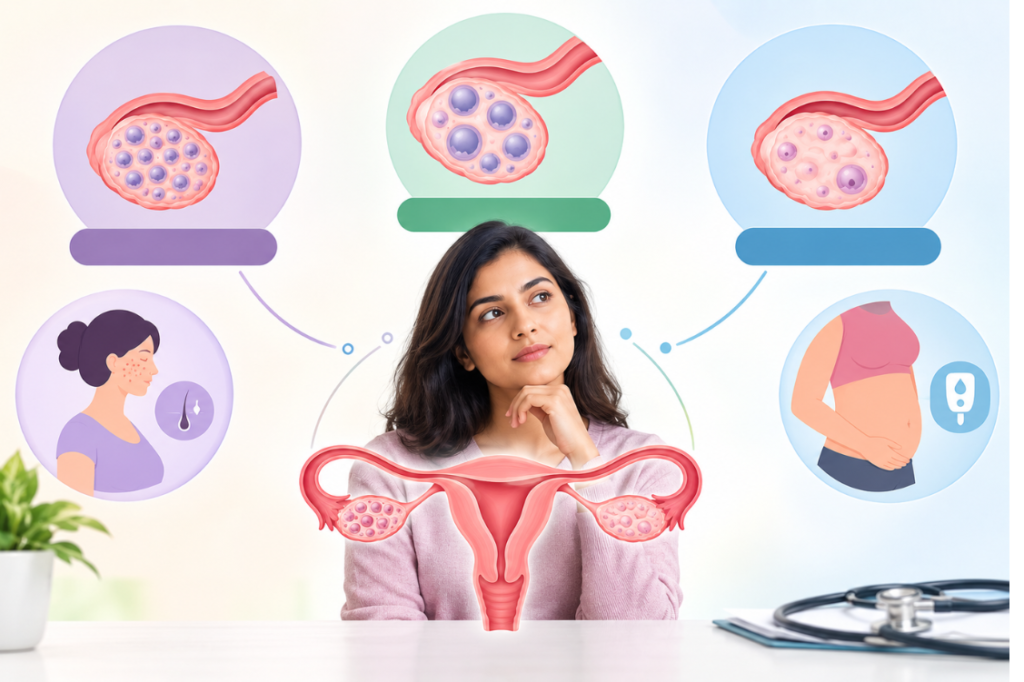
PCOS gets talked about as if it’s a single, uniform condition, but two women with the same diagnosis can have quite different hormonal pictures, symptoms, and — importantly — different treatment priorities. Understanding which pattern fits your situation helps make sense of why your treatment plan might look different from someone else’s PCOS journey.
Why PCOS Is Classified Into Types at All
PCOS is diagnosed based on a combination of features — irregular ovulation, elevated androgen (male hormone) levels or symptoms, and polycystic-appearing ovaries on ultrasound. Not every woman with PCOS has all three in the same proportion, which is why researchers and clinicians have grouped presentations into recognizable patterns, most commonly referenced as four phenotypes.
The Four Recognized Phenotypes
Type A (Classic PCOS): Involves all three core features — irregular ovulation, elevated androgens, and polycystic ovaries on ultrasound. This is generally considered the most complete presentation and is often associated with more pronounced insulin resistance.
Type B: Involves irregular ovulation and elevated androgens, but without the polycystic ovarian appearance on ultrasound. This type also tends to carry a more significant metabolic profile.
Type C (Ovulatory PCOS): Involves elevated androgens and polycystic ovaries on ultrasound, but with regular ovulation. Women with this type may have fewer fertility-related symptoms tied to ovulation itself, though androgen-related symptoms like acne or excess hair growth can still be present.
Type D (Non-Androgenic PCOS): Involves irregular ovulation and polycystic ovaries on ultrasound, but without elevated androgens or their associated symptoms. This type is sometimes considered milder in terms of metabolic risk, though it still affects ovulation and fertility.
Why This Distinction Actually Changes Treatment
For fertility, ovulation-related types (A, B, D) generally need direct intervention — ovulation induction medication — to improve conception chances, while Type C, with already-regular ovulation, may need a different approach if fertility is the concern, since ovulation isn’t the primary obstacle.
For metabolic health, Types A and B, more strongly associated with insulin resistance, often benefit more directly from interventions targeting blood sugar regulation, including specific dietary approaches and medications like metformin, compared to Type D.
For androgen-related symptoms — acne, excess hair growth, hair thinning — Types A, B, and C, all involving elevated androgens, are the ones where anti-androgen treatment approaches are most relevant; Type D generally doesn’t need this specific treatment line since androgens aren’t elevated.
For long-term monitoring, types more closely tied to insulin resistance are generally monitored more closely for related long-term risks, including type 2 diabetes and cardiovascular factors, making this classification relevant well beyond the immediate fertility conversation.
Why Your Own Diagnosis Should Specify More Than Just “PCOS”
A PCOS diagnosis without further detail doesn’t tell you or your specialist enough to build a targeted plan. It’s worth understanding — and asking directly, if it hasn’t been explained — which specific features are driving your diagnosis: is it your ovulation pattern, your androgen levels, your ultrasound findings, or some combination? This detail is what actually shapes whether your treatment plan centers on ovulation induction, metabolic management, androgen-focused treatment, or some combination of these.
How Diagnosis Actually Happens
A proper PCOS evaluation typically includes a menstrual history, blood tests for androgen levels and other relevant hormones, and a pelvic ultrasound to assess ovarian appearance. Since PCOS is diagnosed by combining these findings — and specifically by ruling out other conditions that can mimic it, like thyroid dysfunction — a rushed diagnosis based on symptoms alone, without this full workup, can miss the specific pattern that should be guiding your treatment.
Building a Treatment Plan Around Your Specific Pattern
Once your specific presentation is understood, a treatment plan can be built around what actually matters most for you — whether that’s restoring regular ovulation for fertility, managing insulin resistance for long-term health, addressing androgen-related symptoms, or some combination, rather than a single generic PCOS protocol applied regardless of which features you actually have.
Frequently Asked Question
Some features can shift — for instance, ovulation patterns can change with weight changes or age — but the underlying phenotype is generally a reasonably stable way to understand an individual’s presentation, revisited as needed if symptoms change significantly.
Not necessarily. Even non-androgenic PCOS affects ovulation and fertility and can still benefit from treatment, particularly if you’re trying to conceive — “milder” refers to certain metabolic risk factors, not an absence of anything worth addressing.
It’s one of three criteria typically used, but a diagnosis can sometimes be made with the other two criteria (irregular ovulation and elevated androgens) present, particularly in adolescents, where ultrasound findings are interpreted more cautiously.
A thorough diagnosis generally requires blood tests to assess androgen levels and rule out other conditions like thyroid dysfunction that can cause similar symptoms — diagnosis based on symptoms and ultrasound alone risks missing an important distinguishing factor.